
Table of contents
Table of contents

Need advice before you get started?
Book an appointment

Need advice before you get started?
Book an appointment
Consultation time: a scarce resource under pressure
Medical consultations, whether in town or in hospitals, are at the heart of any healthcare journey, and yet, they are now taking place within increasingly limited time frames.
All over the world, healthcare systems are facing the same tension: medical time is shrinking, while doctors must see more and more patients within a limited consultation time.
In the latest comprehensive international study published in BMJ Open (data up to 2016) covering more than 28 million consultations in 67 countries, it shows that the average length of a primary care consultation varies significantly depending on the healthcare system. It can be extremely short in some countries, such as Bangladesh (48 seconds), or exceed 20 minutes in others, such as Sweden (around 22.5 minutes).
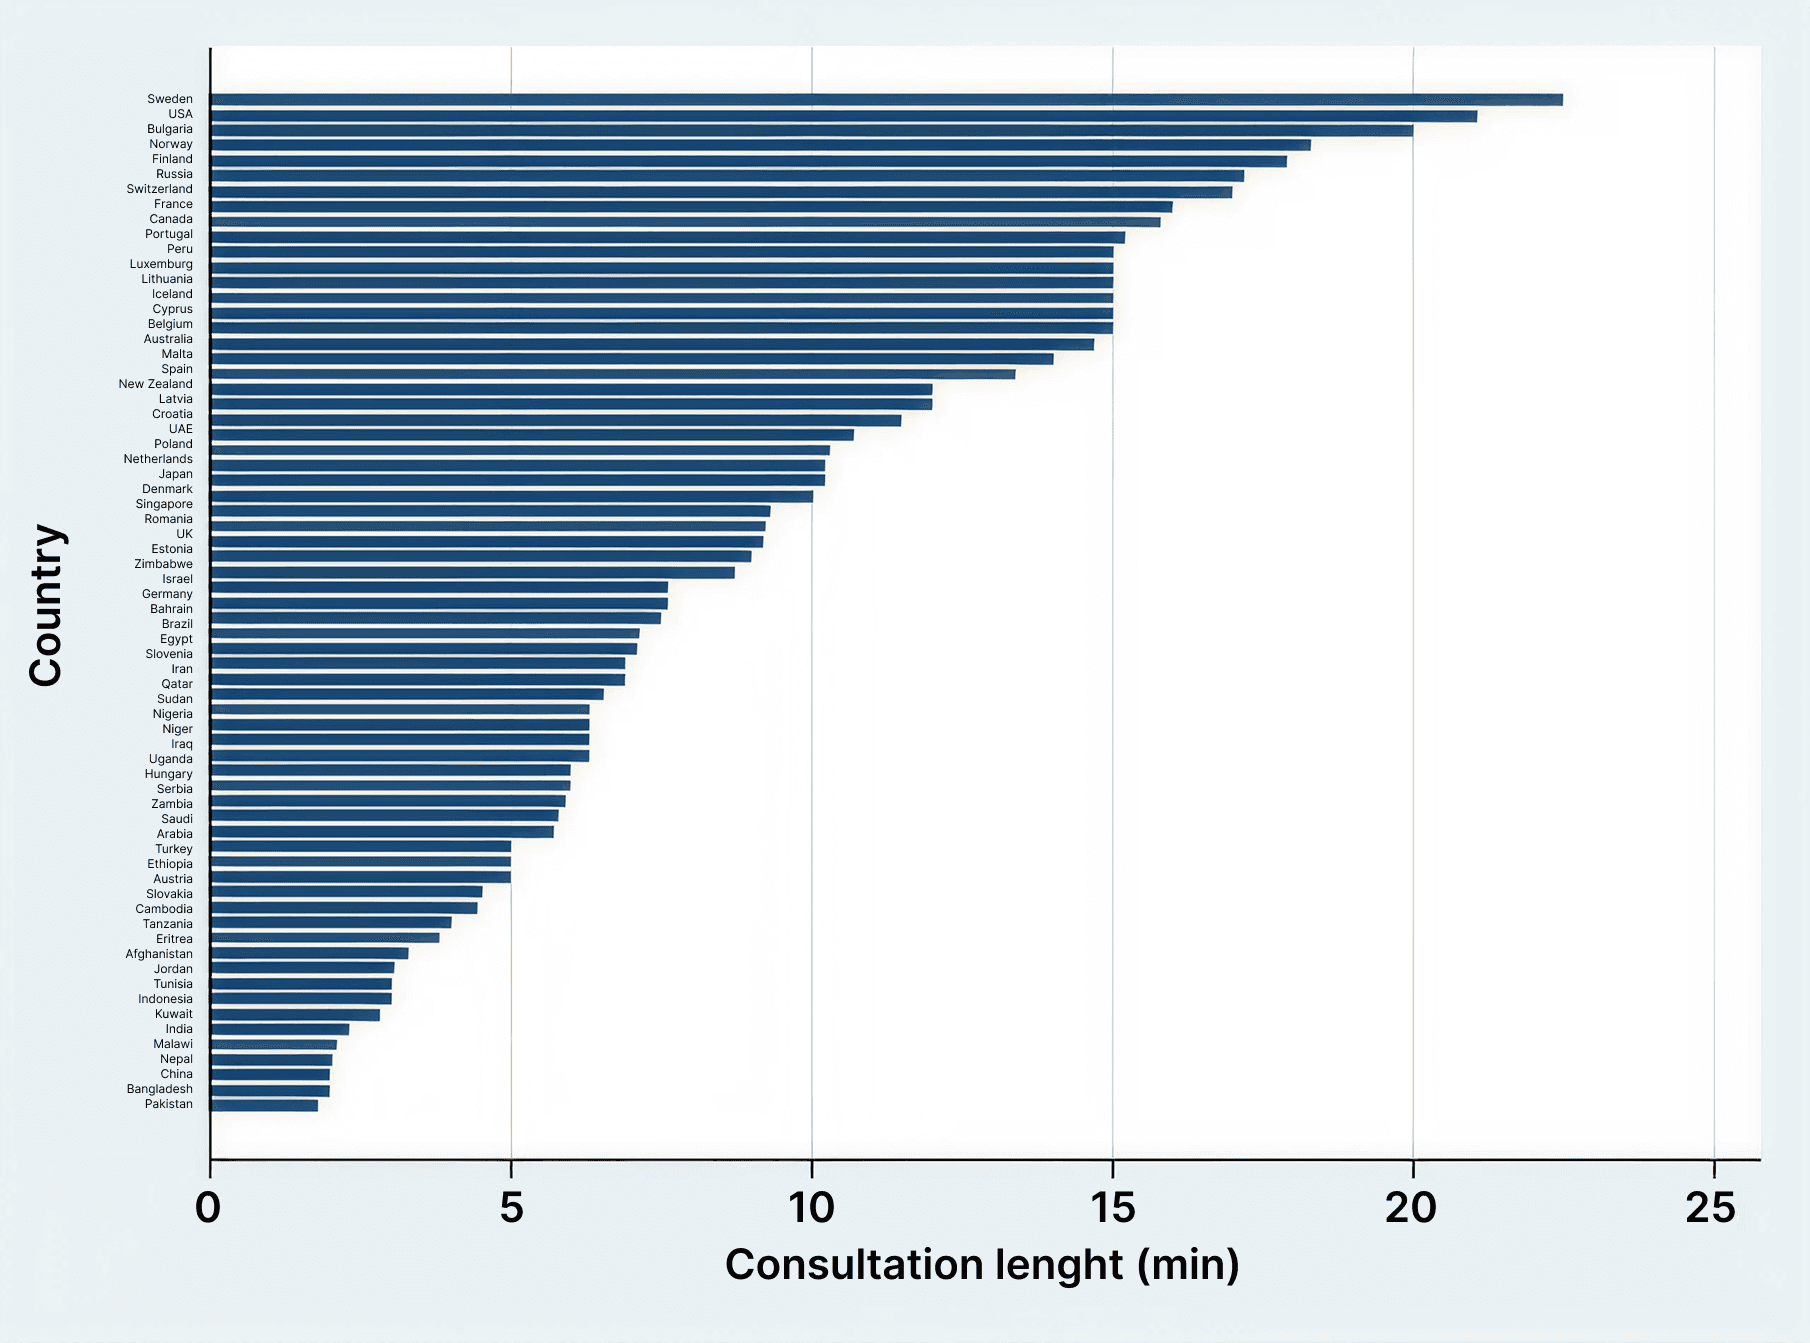
Source: Irving G. et al., International variations in primary care physician consultation time: a systematic review of 67 countries, BMJ Open, 2017.
More recent work sheds light on the underlying mechanisms behind these differences. A review published in 2025 in Health Policy shows that consultation length depends largely on the organization of healthcare systems and payment models, reflecting a trade-off between the time that can be devoted to each patient and the number of patients who need to be seen.
In this global landscape, France is rather a good example, with an average length estimated at around 16 to 18 minutes per consultation according to the latest national estimates from 2019. Rather than reflecting a “good” length, this position reflects a specific need for balance in our healthcare system: this consultation time results from a compromise between the quality of care and the number of patients who can be seen.
And yet, this consultation time is in reality extremely constrained given what it is supposed to contain. In just a few minutes, the doctor must welcome the patient, listen, understand their situation, gather the reason or reasons for the consultation, question them, make sure their medical history is up to date, retrieve any available documents (X-rays, letters, etc.), and carry out a clinical examination when the situation justifies it. Based on these elements, the doctor analyses, reasons, makes decisions, explains the diagnosis (or uncertainty), details the treatment or follow-up to be put in place... And that is not all: they must still complete the medical record, organize the next steps in care, address screening questions when time allows, bill, and see the patient out. All this, in just a few minutes.
Under these conditions, marked by a shrinking amount of medical time, it becomes essential to ask how this time can be better organized to care for the patient in the best possible conditions.
Hence a simple question: must everything that makes up a consultation necessarily be carried out at the time of the consultation, and only by the physician?
How to give medical time back to doctors?
When looking to give time back to doctors, it seems logical to focus on the very structure of the consultation.
In practice, a medical consultation is structured around four main clinical stages, even though, in reality, they are closely intertwined:
understanding the request: welcoming the patient, identifying the reason for the consultation, and bringing the main issue to light;
gathering and structuring clinical information: conducting the questioning, gathering history, ongoing treatments, life context, and performing the clinical examination if necessary;
analysing and deciding: formulating hypotheses, prioritising possibilities, and determining management;
explaining and organising the next steps: informing, prescribing, giving instructions, and structuring the follow-up.
In addition to these stages, there is an essential cross-cutting layer, which is often less visible but time-consuming: documentation, care coordination, and administrative tasks (updating the medical file, prescriptions, certificates, organising the care pathway, billing).
Among these stages, some require the direct expertise of the doctor. Others consist primarily of gathering and structuring information about the patient.
This is particularly true for the medical questioning, also known as anamnesis (often cited as the main delegable element, and yet not the only one). Anamnesis is the structured gathering of the information necessary to understand the patient's situation: history of the problem, symptoms, timeline, background, treatments, allergies, life context, or even risk factors. It forms an essential basis for clinical reasoning.
Depending on the practice context, the organisation of this stage can be carried out directly by the doctor, shared with other healthcare professionals, or, in some cases, prepared beforehand.
Let's look at the example of two neighbouring countries that illustrate other ways of organising certain stages of the consultation that are often solely managed by the doctor in France.
The German model
Since 2006, medical practices have relied on medical assistants called Medizinische Fachangestellte (MFA). These healthcare professionals participate in the organisation of the practice and take on various tasks, including:
patient reception,
administrative management,
gathering medical information before the consultation.
According to data from IRDES, Germany had around 341,000 medical assistants in 2021. In individual practices, there is an average of 3.4 assistants or nurses per doctor, and in group practices, this figure can exceed 8 assistants.
This setup allows for a greater distribution of tasks within the practice and supports medical activity. In its comparison between France and Germany, IRDES also points out that the fact that German doctors employ many assistants and support staff, including in individual practices, seems to contribute to a high volume of activity.
In 2019, the average number of doctor visits was 9.8 per inhabitant in Germany, compared to 5.9 in France. Furthermore, research carried out in Germany also shows concrete benefits from this setup: in general medicine practices, the involvement of trained assistants in the follow-up of chronic patients is associated with a reduction in hospitalisations and hospitalisation costs, as well as a decrease in referrals to certain specialists.
The German model shows that medical time can be managed differently, allowing for both an increase in capacity and an improvement in the quality of healthcare delivery.
The British model
Since the 2010s, the United Kingdom has also developed a multidisciplinary team-work model around general practitioners.
In the public British healthcare system (NHS), general practices rely on expanded teams including nurses, clinical pharmacists, physiotherapists, medical assistants, and other healthcare professionals.
This model was reinforced by the creation of Primary Care Networks in 2019, which aim to pool resources between practices in order to better organise patient care.
The objective is to share certain medical or organisational tasks among different healthcare professionals, in order to streamline the care pathway and improve access to consultations.
According to data from the NHS, more than 37,000 non-medical healthcare professionals work in these expanded primary care teams.
The French situation
In France, the medical assistant model is more recent and is still in development.
The medical assistants scheme was introduced in 2018 as part of the "Ma Santé 2022" strategy, with the aim of freeing up medical time by relieving doctors of a portion of administrative and organisational tasks, increasing the monitored patient base, and improving patients' access to care.
At the beginning of 2022, around 5% of general practitioners worked with a medical assistant according to analyses by IRDES on the organisation of medical practices. Since then, the scheme has been gradually progressing, and according to data from Assurance Maladie, around 7,240 medical assistants were recorded in 2024, and nearly 9,000 in 2025. This progression shows a real momentum. However, these figures still remain below the objectives set by public authorities, which target 10,000 medical assistants in the short term and 15,000 by 2028.
Yet, the deployment of this scheme relies on significant organisational changes within practices, as well as funding and recruitment conditions that can take time to establish.
In other words, even if the scheme is progressing, its development remains gradual and cannot, on its own and in the short term, meet all the needs for optimising care organisation and medical time.
The option of digital innovation and AI in healthcare
Even if the scheme is progressing, it will not be enough on its own. To complement this dynamic, digital technology and AI in healthcare offer another avenue besides merely reorganising practices: better preparing, earlier on, a portion of the consultation.
In other sectors, innovation is no longer limited to "digitising" what already exists: it strengthens useful actions by delivering them at the right time and on a regular basis, sometimes daily.
In healthcare, this logic makes complete sense for repetitive, time-consuming, yet essential tasks, such as information gathering (symptoms, history, treatments, risk factors, prevention details, or useful documents).
Rather than concentrating all this collection at the beginning of the consultation, tools can intervene beforehand, in a gradual manner, via tailored questionnaires. They help the patient formulate and complete information, and allow it to be structured without taking up medical time.
The challenge is therefore not only to collect data, but to support the doctor's work throughout the pathway: before the consultation (preparation), during the discussion (clinical reference points), and after (follow-up, post-consultation).
In one sentence: digital technology and AI in healthcare can be used to shift medical tasks, such as data collection and structuring, beforehand or elsewhere, so that the consultation remains primarily a time for welcoming, analysis, and decision-making.
The doctor begins the consultation with an already organised overview, which facilitates the verification of key points and frees up time for the examination, analysis, decision, and relationship.
At no point do digital technology and AI in healthcare replace the consultation. They assist and can even take over part of the preparation tasks, so that the doctor's time is dedicated where it is most useful.
Concretely, what can be prepared in a medical consultation?
The reason(s) and context: what brings them in, since when, what has already been tried
Symptoms: onset, intensity, location, frequency, worsening and relieving factors.
History and treatments: known illnesses, surgeries, allergies, ongoing treatments, self-medication.
Prevention details: vaccines, screenings, risk factors, lifestyle habits.
Useful documents: latest prescriptions, test results, reports, measurements (blood pressure, blood sugar, etc.).
Preparing for your consultation: what are the benefits?
Anticipating part of the consultation beforehand is not intended to replace the doctor, but to allow them to devote more time to what truly requires their expertise.
With information already structured, the doctor spends less time reviewing the context and can focus on the essentials: checking key elements, guiding the clinical analysis, deciding on care, and strengthening prevention (screenings, advice, monitoring of risk factors).
This organisation also improves the flow of the consultation: important information emerges earlier, which limits last-minute omissions, disorganized consultations, and accumulating delays.
At the scale of the healthcare system, the stakes are just as tangible: by streamlining the organisation of consultations, notably through preparation beforehand, practices can increase their capacity for care.
Data from the Assurance Maladie (French National Health Insurance) thus show that practices using a medical assistant, which allows for delegation and better preparation of certain steps, can monitor more patients: the patient base increases on average by 19.5% over four years, compared to 6.6% without a medical assistant.
In the practices concerned, this represents an average of more than 250 additional patients monitored per doctor. In other words, better organising the consultation improves both the working conditions for doctors and access to care for patients.
Conclusion
The medical consultation will always remain a human moment, based on listening, examination, and clinical decision-making.
But at a time when medical time is becoming a scarce resource, better preparing for this moment seems obvious.
By freeing up time for the essentials, medicine can remain what it has always been: an attentive, rigorous, and deeply human practice.





